
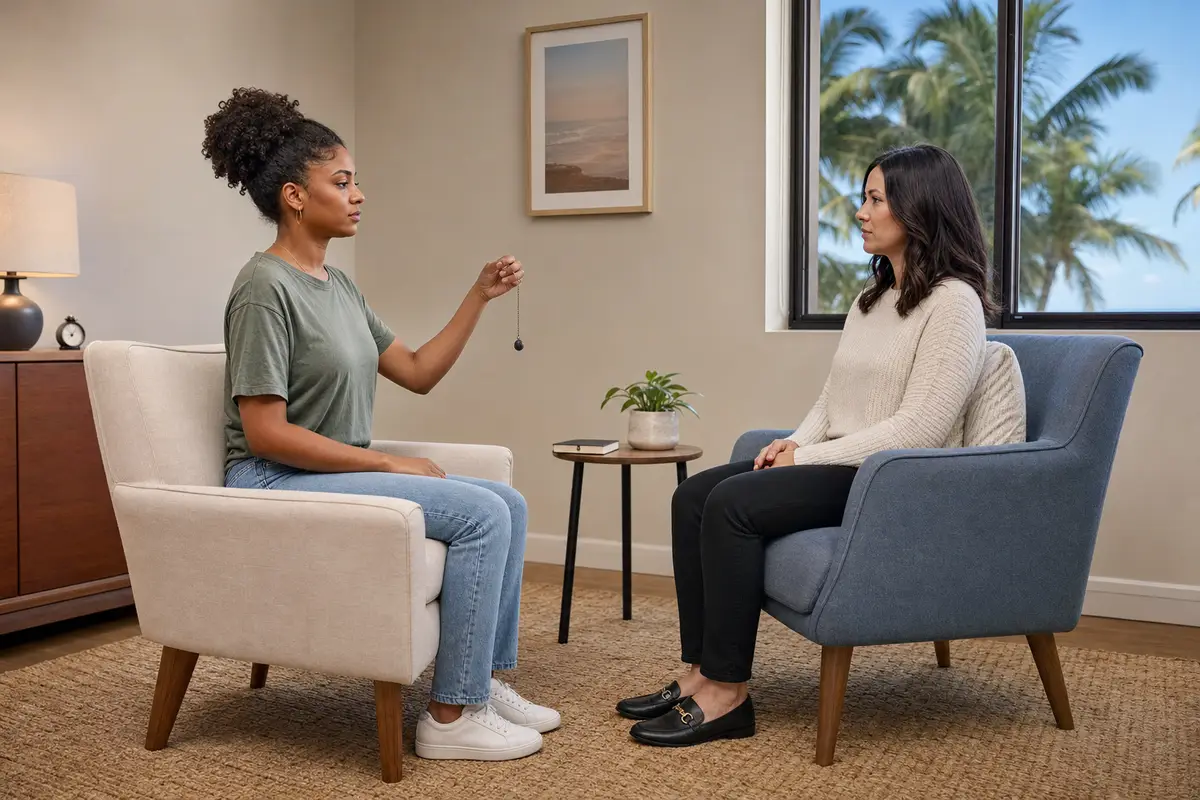
Key Takeaways
- EMDR stands for Eye Movement Desensitization and Reprocessing, a structured therapy approach built specifically for trauma.
- The therapy uses bilateral stimulation, most commonly guided eye movements, while a person briefly recalls a distressing memory, with the goal of reducing its emotional charge.
- EMDR does not require a person to narrate the trauma story in detail the way some talk therapies do.
- Sessions follow an eight-phase structure, from history-taking through reprocessing to closure and reevaluation.
- EMDR is used for single-incident trauma, childhood trauma, and trauma connected to long-term toxic or abusive relationships.
When someone tells you ‘just try EMDR,’ it rarely comes with an explanation of what actually happens in the room. You’re left picturing something between hypnosis and a magic trick, which makes the idea easy to dismiss and hard to trust. If you’re asking what is EMDR trauma therapy because a friend, a doctor, or your own research keeps bringing up the name, you deserve a clear answer before you decide anything.
This guide walks through the mechanism, the session structure, and who the approach is built for, so you can evaluate it on facts instead of secondhand impressions. It also covers what a first conversation with a clinician looks like, because knowing the structure in advance changes how it feels to walk in.
What is EMDR trauma therapy, exactly?
EMDR trauma therapy is a structured, phase-based approach that helps the brain process memories that got ‘stuck’ during or after a distressing event. The name stands for Eye Movement Desensitization and Reprocessing. A trained clinician guides the client through brief recollections of a difficult memory while directing a form of bilateral stimulation: side-to-side eye movements, tapping, or alternating sounds.
The underlying idea is that trauma memories do not get filed away the way ordinary memories do. Instead of becoming a memory a person can recall without being flooded by it, the event stays raw: the images, body sensations, and emotional charge stay close to the surface, ready to resurface with the wrong trigger. EMDR is designed to help the brain complete that filing process, so the memory becomes something a person has lived through rather than something still happening to them.
This differs from therapies built around talking through the narrative in detail. A person doing EMDR does not need to describe the trauma at length or relive it moment by moment to benefit. That distinction matters for people who have avoided therapy specifically because they dread retelling the story. For a broader look at how trauma-focused approaches compare, this overview of trauma therapy covers several models side by side.
The approach has a specific target: the memory network itself, not just the thoughts a person has about that memory. That is the core mechanical difference from therapies built around discussion and reframing alone. A clinician measures progress by tracking how the target memory changes across sessions, not by how fluently a person can describe it.
How an EMDR session actually works
An EMDR session follows a defined sequence, not a loose conversation. Clinicians trained in the method use an eight-phase structure, built to keep the process safe and predictable for the client. Each phase has its own goal and its own stopping point before the next one begins.
The eight phases, briefly
- History taking: the clinician learns about the person’s background, current symptoms, and which memories are driving distress.
- Preparation: the clinician explains the process and builds coping tools the client can use if a memory feels overwhelming.
- Assessment: client and clinician identify a specific target memory, along with the negative belief attached to it (for example, ‘I am not safe’) and the positive belief they want to move toward (‘I am safe now’).
- Desensitization: the client briefly holds the memory in mind while following the clinician’s guided eye movements or other bilateral stimulation, in short sets, pausing to check in between.
- Installation: the clinician helps strengthen the new, more accurate belief in place of the old one.
- Body scan: the client notices any remaining physical tension connected to the memory.
- Closure: each session ends with a return to emotional stability, regardless of where the processing landed.
- Reevaluation: the next session begins by checking how the memory and its charge have shifted since the last one.
A single memory can take more than one session to fully process, particularly when the trauma is layered or long-standing. How long does trauma therapy take walks through what realistically shapes that timeline.
Each phase has a defined stopping point. A clinician does not move from desensitization to installation until the target memory’s distress rating has dropped to a specific, client-reported level. That structure is what separates EMDR from an open-ended conversation about a hard memory. The client, not the clock, determines when a phase is complete.
What EMDR is treating, specifically
EMDR was developed for single-incident trauma, such as a car accident or an assault, and its use has since expanded well beyond that. Clinicians now use it for childhood trauma, combat-related trauma, and the cumulative harm caused by years inside an abusive or controlling relationship.
Consider someone who grew up with a parent who alternated between affection and cruelty, never letting the child predict which one was coming. That person reaches adulthood with a nervous system wired for threat, even in relationships that are objectively safe. EMDR targets the specific memories underneath that wiring rather than only addressing the present-day anxiety. For readers trying to connect current patterns to a parent’s behavior, this guide to recognizing a narcissistic parent is a useful starting point.
The same logic applies to adults untangling themselves from a toxic adult relationship. Someone who spent years dating a narcissist carries specific memories, a particular fight, a specific humiliation, that keep replaying involuntarily. EMDR works directly with those memories rather than only managing the anxiety they produce day to day.
The distinction matters because managing anxiety and reprocessing the memory that produces it are two different clinical goals, and they call for different tools. A clinician decides which goal to prioritize first based on what the history-taking phase reveals.
How EMDR differs from talk therapy
Traditional talk therapy relies heavily on verbal processing: describing events, examining thoughts, and working through emotions out loud over time. EMDR uses that same groundwork, history, goals, trust, and adds a structured reprocessing component that does not depend on extensive verbal narration of the trauma itself.
This makes EMDR a meaningful option for people who find detailed storytelling about their trauma retraumatizing, or who have tried talk therapy and found that insight alone did not change how their body reacted to triggers. Understanding a trauma intellectually and no longer reacting to it physically are two different outcomes, and EMDR is built to address the second one directly.
EMDR is not a replacement for a trauma-informed therapeutic relationship; it is a technique used within one. A clinician still needs to understand the full context of a person’s history and current life to use EMDR safely and effectively. What is a trauma-informed therapist explains what that foundation looks like in practice, regardless of which specific method a clinician uses on top of it.
Signs EMDR, or trauma therapy generally, is worth exploring
Some people know they have trauma history but are not sure it affects them enough to need therapy. Others feel affected daily but cannot name why. A few patterns worth paying attention to: recurring intrusive memories, a strong physical reaction to reminders of a past event, difficulty trusting people who have not given a reason for distrust, and emotional responses that feel disproportionate to the present situation.
When several of these sound familiar, this self-check on signs you may need trauma therapy offers a more complete picture. People recovering from a pattern of toxic family members or a broader toxic relationship recognize themselves here, even after years spent explaining their reactions as personality rather than history. Naming the pattern is often the first concrete step toward deciding whether to pursue therapy at all.
Why EMDR can feel hard before it feels helpful
EMDR asks a person to briefly touch a painful memory on purpose, which understandably feels counterintuitive. The preparation phase exists precisely because this part is hard: clinicians build coping skills before asking a client to approach difficult material, and sessions are structured so no one leaves in a worse state than they arrived.
Trauma therapy of any kind, EMDR included, is rarely comfortable in the early stages. Why trauma therapy is so hard addresses this directly, because understanding that difficulty is part of the process, not a sign something is going wrong, changes how people stick with it.
The discomfort is front-loaded by design. The eight-phase structure exists specifically to keep the hardest part, the desensitization phase, contained and time-limited rather than open-ended. A session closes with stabilization every time, so the hard work has a defined edge around it.
How to talk to a therapist about starting EMDR
You do not need to arrive with a polished narrative or know which memories to target. A clinician trained in EMDR asks structured questions during the history-taking phase to identify target memories collaboratively. If you are nervous about how to begin that conversation at all, how to talk about trauma in therapy offers a practical starting point regardless of which specific method your therapist uses.
For people still in or recently out of a harmful relationship, timing matters. Starting trauma-focused work while still in regular contact with the person who caused the harm complicates treatment. How to leave a narcissist and signs of a toxic relationship are worth reading first if that applies to your situation.
Common questions about EMDR trauma therapy
Does EMDR work for childhood trauma specifically?
Yes. EMDR is widely used for childhood trauma, including experiences a person did not label as traumatic until adulthood. Childhood trauma in adults shows up as relationship patterns, anxiety, or emotional numbness rather than clear memories, and EMDR targets the specific underlying events even when a person initially sought therapy for something that seemed unrelated.
How many sessions does EMDR usually take?
The number varies by person and by how many distinct memories need processing. Single-incident trauma can take a handful of sessions to process fully. Complex or childhood trauma involves more memories, which generally extends the number of sessions required. How long does therapy take for childhood trauma breaks down the factors that affect this timeline in more detail.
Is EMDR the same as trauma-informed therapy?
No. Trauma-informed therapy describes an overall approach and framework a clinician brings to all of their work, recognizing how trauma affects a person’s nervous system, trust, and behavior. EMDR is a specific technique that a trauma-informed clinician uses within that framework. What is trauma-informed therapy explains the broader framework in more depth.
Can I take a self-assessment before deciding on EMDR?
A self-assessment gives you a list of experiences to bring into a first appointment; it is not a diagnosis. A childhood trauma test clarifies which experiences you want to bring up with a clinician, who then determines whether EMDR or another approach fits your specific history.
Does EMDR replace medication for trauma symptoms?
EMDR is a therapy approach, not a medical treatment, and it does not involve medication decisions. Questions about medication belong with a prescribing physician or psychiatric provider, separate from the therapy itself.
If you or someone you know is in immediate danger, call or text 988 (Suicide & Crisis Lifeline).
What getting started looks like
Understanding what EMDR trauma therapy involves is one thing; finding a clinician trained to deliver it is another. How does trauma therapy work in practice depends heavily on the specific clinician’s training, not just the method’s name, so ask directly about EMDR certification when you reach out.
Better You Therapy is a Florida-licensed mental health practice providing teletherapy statewide and on-site clinical services in Southeast Florida senior-living communities. Clinicians are available to discuss whether EMDR fits your history, with no referral required to start a conversation. Learn more about our approach to trauma and what the first step looks like.


